



OSHA requirements for EMS today center on three standards: HAZWOPER at 29 CFR 1910.120(q), Bloodborne Pathogens at 29 CFR 1910.1030, and medical services and first aid at 29 CFR 1910.151. Employers must complete a written hazard assessment, maintain a current exposure control plan, train personnel to the right level, supply appropriate PPE, and follow through on post-exposure evaluation and documentation. OSHA’s proposed Emergency Response standard would add to these obligations. Agencies that get the fundamentals right now will have less ground to make up later.
TL;DR:
- Properly classifying incidents is crucial, as HAZWOPER applies only to certain hazardous substance responses, while bloodborne pathogens cover needle-related exposure.
- Training levels should match realistic exposure scenarios, with distinct requirements for awareness, operational, and technical responders, and PPE tied to hazard certainty.
- Maintaining comprehensive documentation, including hazard assessments, training records, and exposure logs, is vital for OSHA compliance and often a primary inspection focus.
- The proposed OSHA Emergency Response standard will soon require EMS agencies to implement formal response plans, hazard assessments, medical screening, and behavioral health resources.
- Conducting a thorough internal gap analysis against current standards and upcoming regulations helps agencies proactively address compliance and avoid inspection issues.
Table of Contents
- Which OSHA standards most often apply to EMS operations
- What training and PPE does OSHA require for EMS?
- What documentation do EMS employers need for OSHA compliance?
- What would OSHA’s proposed Emergency Response rule change?
- Practical compliance checklist for EMS agencies
- PSCG’s perspective on prioritizing OSHA compliance work
- How PSCG helps EMS agencies close OSHA compliance gaps
- Sources
- FAQ
Which OSHA standards most often apply to EMS operations
EMS agencies rarely operate under a single rule. They work inside a web of standards that each cover a different slice of the job, and knowing which one governs which call is half the compliance battle.
- HAZWOPER, 29 CFR 1910.120(q): Covers emergency response to hazardous substance releases. OSHA has clarified that this section applies to emergency response operations for hazardous substance releases, but incidental releases generally fall outside it, so the right classification depends on the anticipated role of your crew, as described in OSHA’s guidance for protecting EMS responders.
- Bloodborne Pathogens, 29 CFR 1910.1030: Requires an exposure control plan, annual training, hepatitis B vaccination access, and a defined post-exposure follow-up process.
- Medical services and first aid, 29 CFR 1910.151: Requires adequate first-aid supplies and ready availability of trained personnel or medical consultation, spelled out in OSHA’s standard for medical services and first aid.
- Respiratory protection, 1910.134, and PPE, 1910.132: Govern respirator programs and the broader duty to select and maintain protective equipment for the hazards your crews actually face.
Each standard has its own trigger. A crew treating a patient exposed to an unknown chemical falls under HAZWOPER. A crew starting an IV falls under Bloodborne Pathogens. Every crew, every shift, falls under 1910.151.
What training and PPE does OSHA require for EMS?
Training level should match the exposure your personnel realistically face, not the worst-case scenario your agency hopes never happens. OSHA recognizes three tiers for hazardous materials response: first responder awareness, first responder operations, and skilled support personnel.
- First responder awareness covers recognizing a hazardous materials incident and initiating a call for qualified help, with no hands-on decontamination duties.
- First responder operations applies when personnel may treat victims who have been only superficially decontaminated or not decontaminated at all. OSHA’s own interpretation letter on HAZWOPER training for EMS ties that role to a minimum of 8 hours of training.
- Skilled support personnel covers specialized responders brought in for a specific technical task, typically with site-specific briefing rather than full HAZWOPER certification.
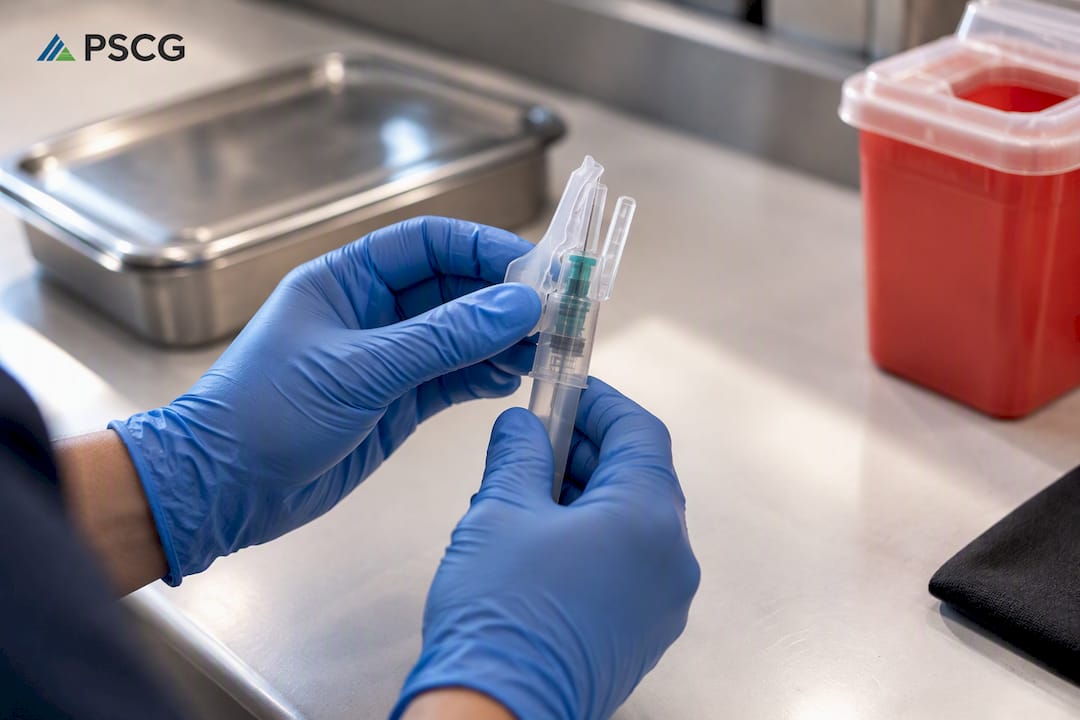
PPE decisions follow the same logic. When the identity or concentration of a contaminant cannot be confirmed, agencies should treat the atmosphere as immediately dangerous to life or health and select SCBA or higher-level protection accordingly. Incident command can authorize lower-level PPE once air monitoring or hazard identification supports it. Under the Bloodborne Pathogens standard, employers also carry a duty to provide engineering controls, like safer sharps devices, not just training. Respirator programs need medical clearance, annual fit testing, and a documented maintenance schedule to hold up under review.
Pro Tip: Involve frontline paramedics and EMTs when selecting safer medical devices. OSHA’s own guidance notes that engineering controls work best when the people using them help choose them, not just when they’re handed down from an office.
What documentation do EMS employers need for OSHA compliance?
Training and equipment mean little without paperwork to back them up. OSHA’s rule at 1910.132(d)(2) requires a written certification that a hazard assessment was actually performed, and this is one of the most common gaps found during EMS inspections, according to OSHA’s guidance for protecting EMS responders.
- Certify the hazard assessment in writing, with the date, the identity of the person performing it, and the specific workplace evaluated.
- Review and update the exposure control plan annually, with input from the frontline staff who actually encounter blood and body fluids on calls.
- Confirm hepatitis B vaccination is offered to all at-risk personnel, not just new hires.
- Initiate post-exposure evaluation and follow-up as soon as possible after an incident. OSHA’s standard interpretation on Bloodborne Pathogens confirms employers must make a good-faith effort to obtain source-patient information as part of that process.
- Keep exposure records confidential and retained for the duration OSHA specifies.
One caveat worth flagging: OSHA standards generally don’t apply to volunteers unless your state operates its own OSHA-approved state plan that extends coverage to them. Agencies in Connecticut and other state-plan jurisdictions should confirm their specific volunteer coverage rules rather than assuming federal defaults apply.
What would OSHA’s proposed Emergency Response rule change?
OSHA published a Notice of Proposed Rulemaking for a new Emergency Response standard on February 5, 2024, and it represents the most significant shift EMS agencies have seen in this area in years. The Federal Register notice for the Emergency Response NPRM proposes expanding scope beyond fire brigades to explicitly cover EMS and technical rescue operations.
That expansion matters because current fire-brigade-focused rules leave gaps for agencies that only run EMS. The proposed standard would add several programmatic elements EMS agencies don’t currently have to formalize:
- Written emergency response plans specific to the agency’s service area and risk profile.
- Hazard vulnerability assessments performed on a recurring basis, not just once.
- Medical screening and surveillance tied to physical demands of the job.
- Access to behavioral health resources for responders.
The proposal is built to align with NFPA and FEMA consensus standards. This means agencies already following those frameworks will have a shorter runway to full compliance if the rule is finalized. Everyone else should treat this as a signal to start closing gaps now: run a gap analysis against the NPRM’s proposed elements, update policies where they’re thin, and refresh training curricula before a compliance deadline forces the pace.
Practical compliance checklist for EMS agencies
Turning OSHA’s requirements into daily practice comes down to a short list of concrete tasks, most of which can be completed within a single quarter if leadership prioritizes them.
- Conduct and certify a written hazard assessment covering every role and vehicle type in your fleet.
- Draft or update your exposure control plan, with frontline input and a documented annual review date.
- Verify bloodborne pathogens training is current and hepatitis B vaccination is offered to every eligible employee.
- Stand up a respirator program with medical clearance, fit testing, and a maintenance log.
- Inventory PPE by vehicle and station, and document replacement schedules.
- Define your post-exposure protocol, including who employees call first and how the designated infection control officer (DICO) is notified.
- Schedule a gap analysis against both current standards and the proposed Emergency Response rule.
Keep a single compliance folder per station or shift containing your hazard assessment certification, exposure control plan, fit-test records, training rosters, and exposure log. Inspectors and DICOs consistently find this format the easiest to review, and it saves your team from scrambling when a records request lands.
Pro Tip: Don’t wait for an OSHA visit to find your documentation gaps. A structured gap analysis, run internally or with outside support, almost always surfaces the same certification and recordkeeping issues inspectors look for first.

PSCG’s perspective on prioritizing OSHA compliance work
Hazard assessments come first, always. A written, certified assessment tells you what training and PPE you actually need, rather than guessing. Agencies that align their policies to NFPA and FEMA consensus standards now will face a far lighter lift when OSHA’s Emergency Response rule is finalized. That’s not a hedge. It’s the more efficient path.
— Mike
How PSCG helps EMS agencies close OSHA compliance gaps
A consulting firm gives EMS agencies a faster path to full compliance than trying to interpret CFR sections and NPRM language alone. The team brings direct field experience to hazard assessments, exposure control plan drafting, and training design, so you’re not starting from a blank page or guessing at what an inspector wants to see.
Our Operational Risk Reduction service is built specifically to help agencies perform the hazard assessments, exposure control plan updates, and respirator program work covered in this article. Professional Education Services for training design and policy drafting, and Experienced EMS Expert Witness support are also offered to assist agencies navigating compliance disputes. If your last hazard assessment predates the current OSHA emphasis on documentation, or if the Emergency Response NPRM has you wondering where your policies stand, visit Thepscgroup to schedule a gap analysis and see where your agency stands today.
Sources
- OSHA standard interpretation — HAZWOPER training for EMS (2017-03-31)
- 1910.151 — Medical services and first aid (OSHA)
- Federal Register — Emergency Response NPRM (Feb 5, 2024)
FAQ
Do OSHA requirements apply in all states?
Federal OSHA standards apply directly in most states, but some states and territories run their own OSHA-approved state plans that can set requirements at least as strict as federal rules. Connecticut and other state-plan jurisdictions may extend coverage to public-sector employees, including some volunteer EMS personnel, in ways federal OSHA does not.
What are the OSHA compliance updates coming for EMS?
The biggest pending change is the proposed Emergency Response standard, published as an NPRM in February 2024, which would formally bring EMS into scope alongside fire brigades. It would add written emergency response plans, recurring hazard vulnerability assessments, medical screening, and behavioral health access as required program elements.
What is the OSHA 6 foot rule?
There is no standalone “6 foot rule” under general OSHA regulations for EMS operations. The phrase is often confused with pandemic-era public health guidance or with specific distance requirements found in other standards, such as electrical safety or fall protection, so agencies should check the specific standard that applies to the hazard in question rather than assume a universal 6 foot rule exists.
What are OSHA 10 requirements?
OSHA 10 refers to a 10-hour general industry or construction safety awareness course, not a specific EMS regulation. It is not a substitute for HAZWOPER training or the Bloodborne Pathogens training required under 1910.1030, though some agencies use it as a supplemental safety orientation for new hires.
How can EMS agencies prepare for OSHA inspections?
Keep a single compliance folder per station with your certified hazard assessment, exposure control plan, fit-test records, training rosters, and exposure log, since this format is what inspectors typically review first. Thepscgroup’s Operational Risk Reduction service can run a gap analysis to identify missing documentation before an inspector does.



